

Stroke Warning Signs: B.E. F.A.S.T. and Treatment Windows
I want to start with the number I had wrong in my head.
For years, if you had asked me what to do when someone’s speech suddenly slurs, I would have given you a confident answer. Check the smile, check the arms, check the speech. And then the part I was proudest of knowing: you have three hours.
Two of those three things were fine. The number was wrong, and the checklist was incomplete.
The stroke warning signs most of us memorized leave out roughly four in ten strokes in one part of the brain. And the three-hour figure is a leftover from the original trials of the 1990s — current American Heart Association / American Stroke Association guidance puts the standard clot-dissolving window at 4.5 hours, with imaging-selected treatment stretching to 9 hours for the drug and 24 hours for mechanical clot removal in certain patients.
But I want to be careful here, because that correction can be read exactly backwards.
Longer windows are not permission to wait. They are eligibility ranges a hospital stroke team decides on, using scans you cannot do at home. Every minute still costs brain tissue. The reason to know the real numbers isn’t so you can take your time — it’s so nobody in your family ever looks at the clock, sees hour five, and decides it’s too late to call.
It is never too late to call 911.
Photo: Image Hunter / Pexels
What a stroke actually is
A stroke is a sudden interruption of blood flow to part of the brain. It comes in two forms.
Ischemic stroke — a clot blocks an artery. This is about 87% of all strokes, and it’s the type that clot-dissolving drugs and mechanical clot removal are designed to treat.
Hemorrhagic stroke — a vessel ruptures and bleeds into or around the brain. A smaller share, but disproportionately deadly. Cleveland Clinic notes these cause severe symptoms that worsen quickly and are frequently fatal or permanently disabling without fast care.
Here is the part I had backwards. I assumed the damage was done the moment it started — that a stroke happened, and then you lived with the result.
That is not how it works.
Around the core of dead tissue sits an area called the penumbra: brain tissue that is starving but not yet dead, and still salvageable for hours in some patients. Modern brain imaging exists largely to find that tissue. How much of a stroke becomes permanent depends heavily on how fast blood flow is restored.
Which is why the phrase “time is brain” isn’t a slogan. It has been measured. In a landmark 2006 analysis published in Stroke (Saver, “Time Is Brain — Quantified”), an untreated large-vessel ischemic stroke destroys an average of 1.9 million neurons per minute — and the ischemic brain ages roughly 3.6 years for every hour without treatment. The AHA’s May 2026 American Stroke Month materials put it in plainer language: nearly 2 million brain cells die every minute during an untreated stroke.
For scale, the CDC reports more than 795,000 Americans have a stroke each year — someone every 40 seconds — and stroke reduces mobility in more than half of survivors aged 65 and older. That last figure is why this sits squarely in senior health.
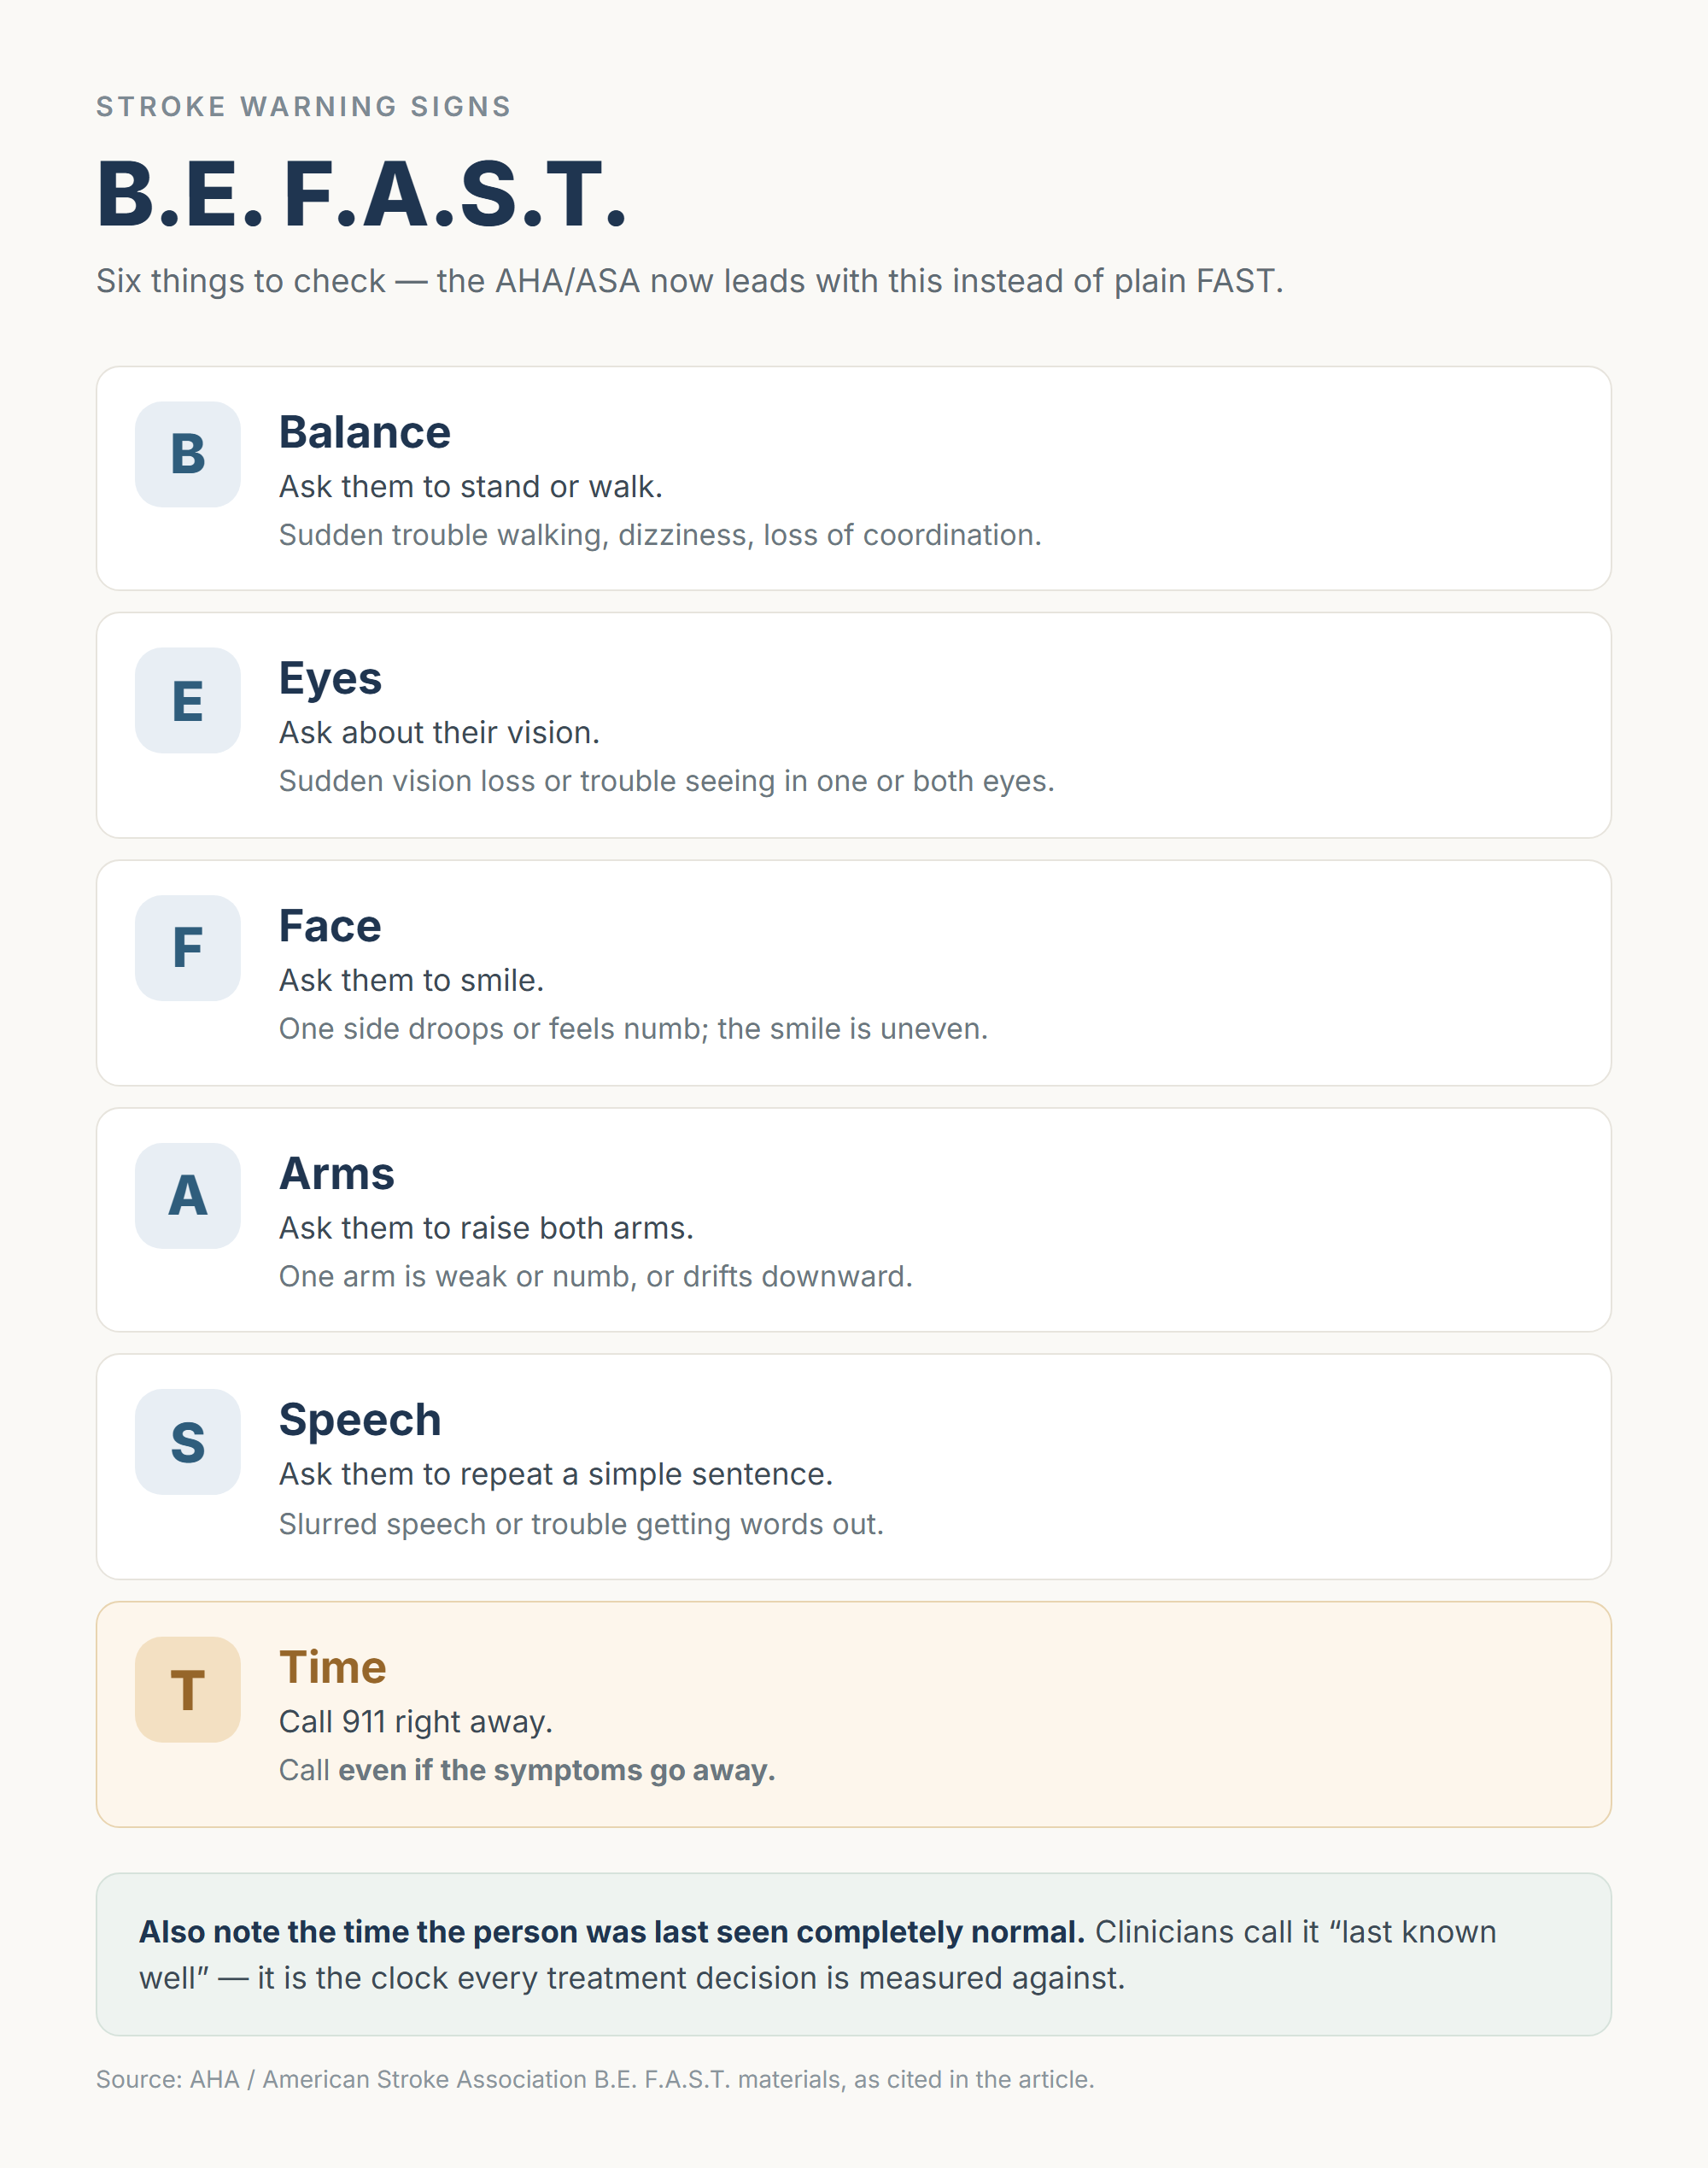
B.E. F.A.S.T. — the six things to check
The mnemonic got longer, and for a good reason. The AHA/ASA now leads with B.E. F.A.S.T. rather than plain FAST.
| Letter | What to check | What it looks like |
|---|---|---|
| B — Balance | Ask them to stand or walk | Sudden trouble walking, dizziness, loss of coordination |
| E — Eyes | Ask about their vision | Sudden vision loss or trouble seeing in one or both eyes |
| F — Face | Ask them to smile | One side droops or feels numb; the smile is uneven |
| A — Arms | Ask them to raise both arms | One arm is weak or numb, or drifts downward |
| S — Speech | Ask them to repeat a simple sentence | Slurred speech or trouble getting words out |
| T — Time | Call 911 right away | Call even if the symptoms go away |
Two details in that table do the heavy lifting, and they’re the ones people skip.
The first is that T includes calling when symptoms disappear. More on that below, because it’s the single most common way this gets missed.
The second is quieter but just as important. Note the time the person was last seen completely normal. Clinicians call this “last known well,” and it is the clock every treatment decision is measured against — not the time you noticed, not the time you called. If they were fine at dinner and slurring at nine, say that. It is genuinely one of the most useful things a family member can bring to an emergency room.
What plain FAST misses
This is the section that changed how I think about the whole subject.
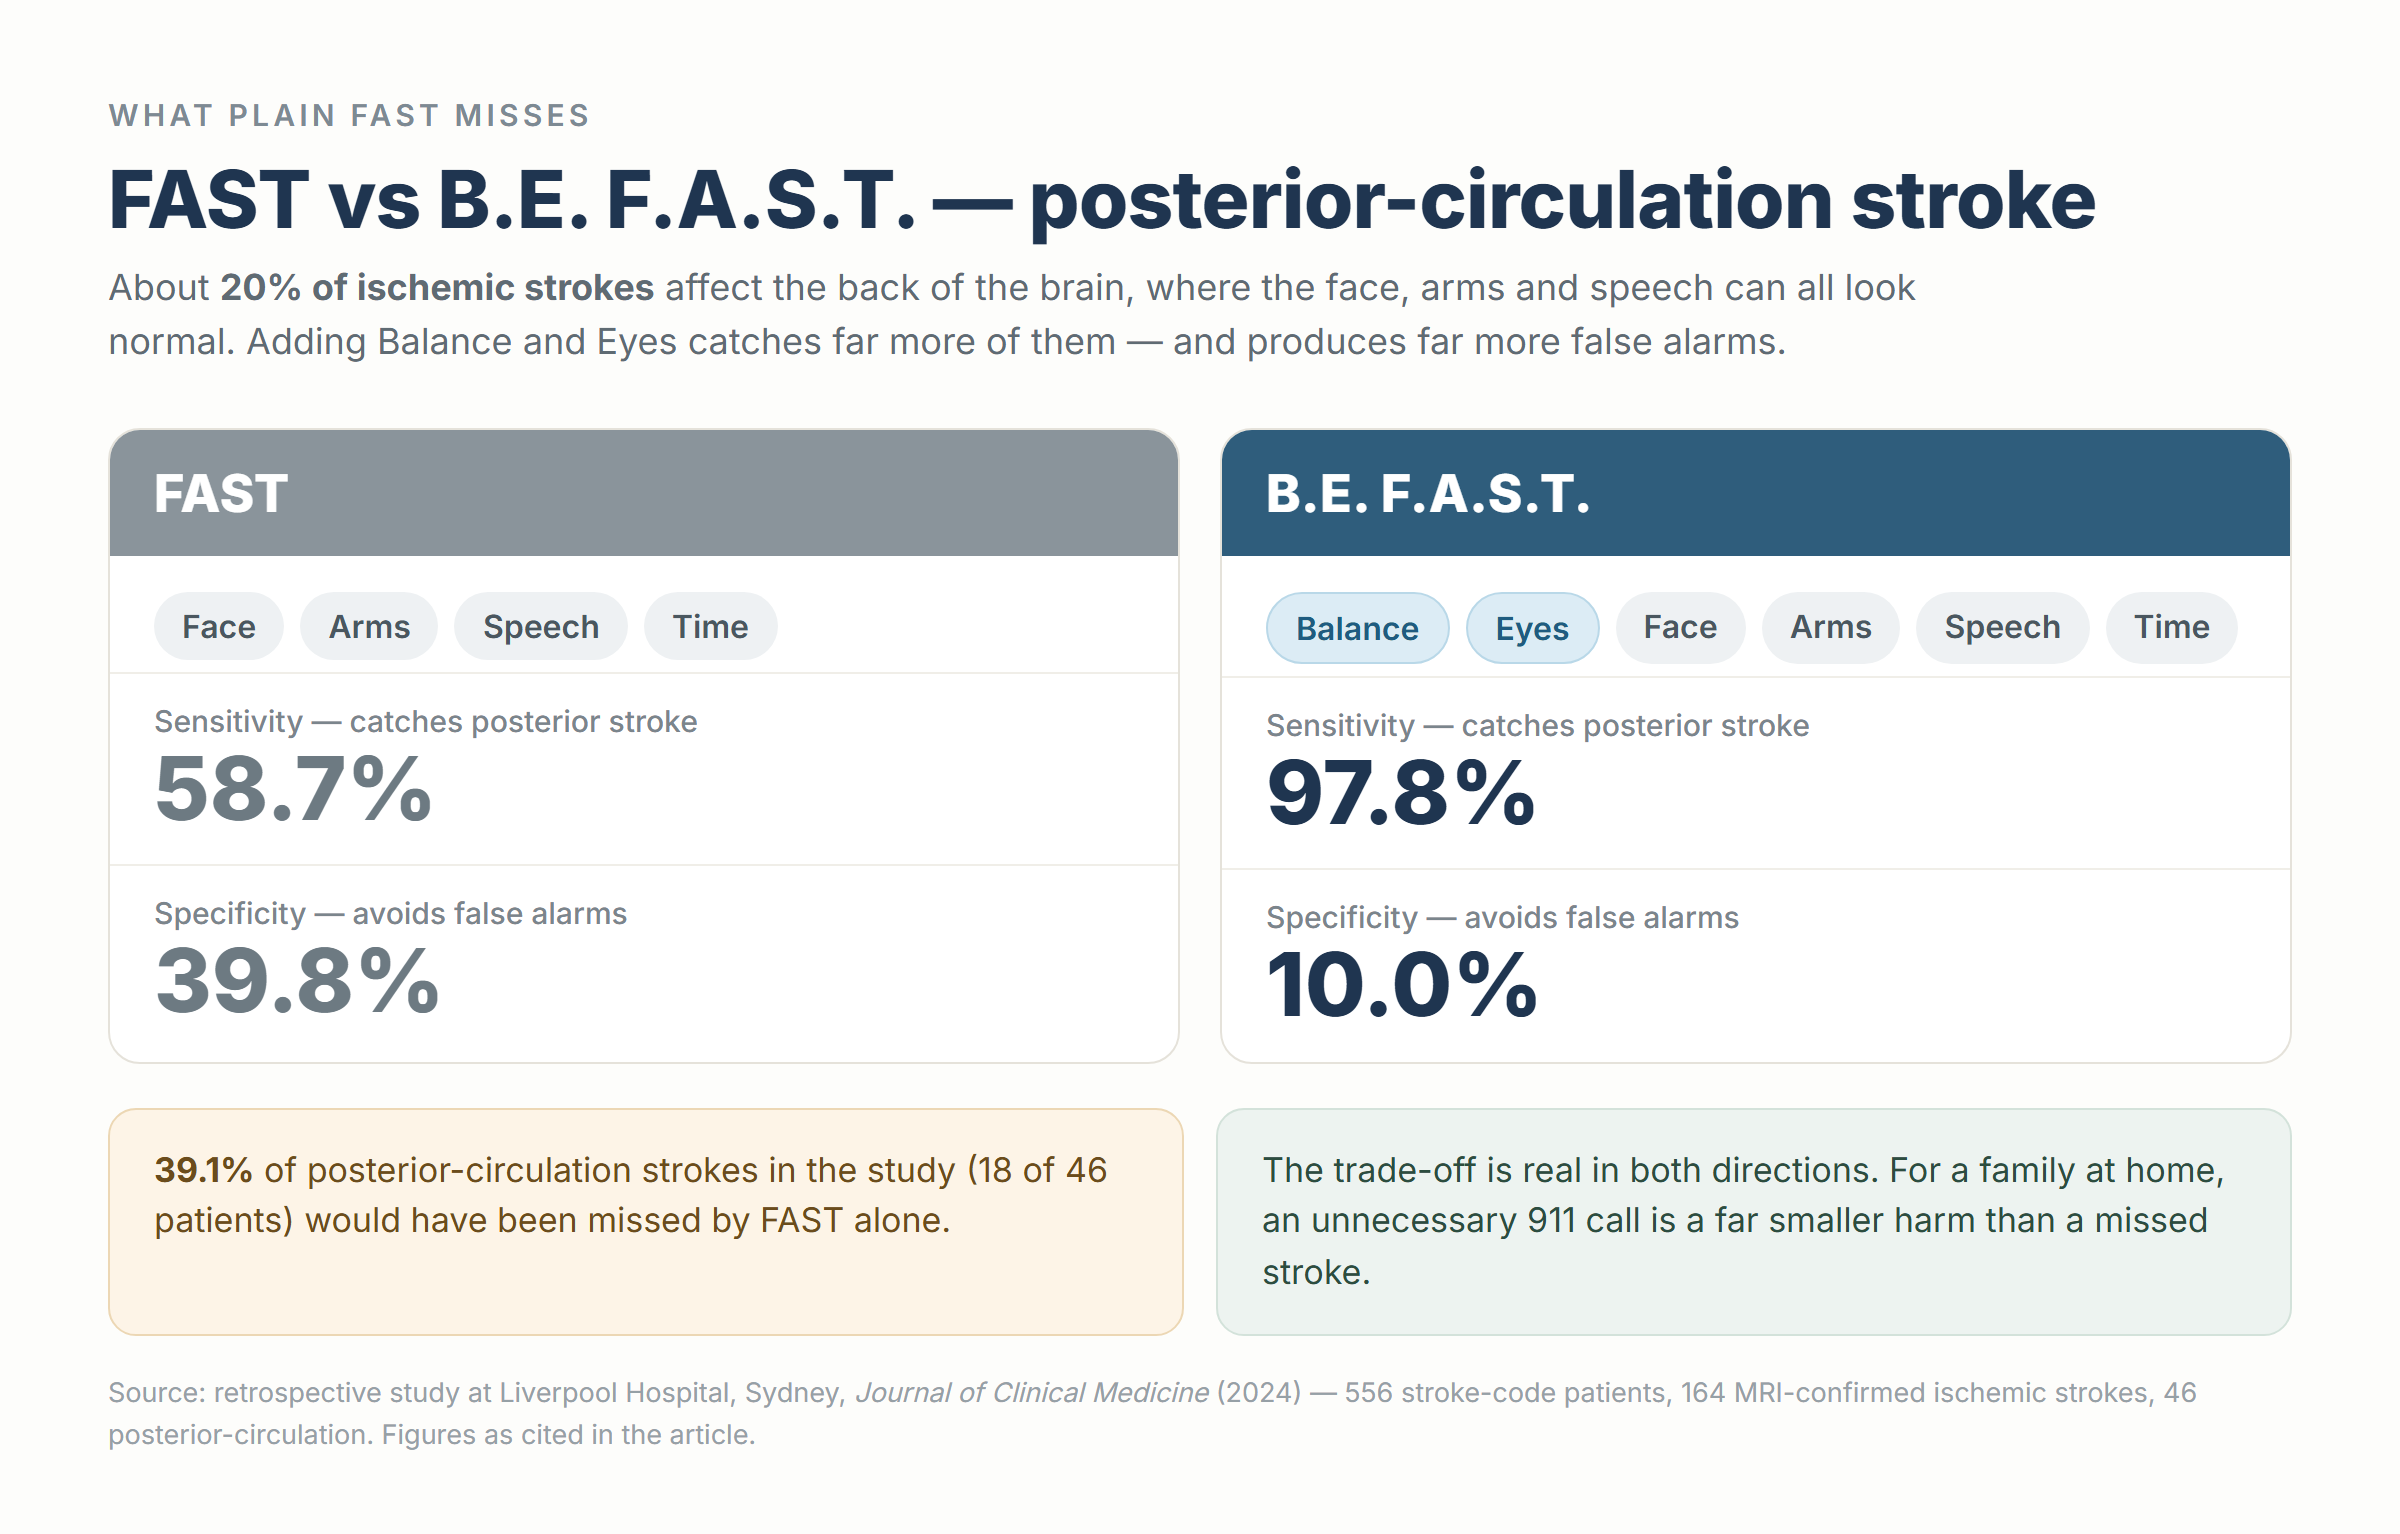
Face, arms, speech — the classic three — are mostly signs of a stroke in the front of the brain. But roughly 20% of ischemic strokes are posterior-circulation strokes, affecting the back of the brain, and they announce themselves completely differently: dizziness and vertigo, imbalance and gait failure, visual disturbance, incoordination, headache.
Someone having one of those can smile normally, hold both arms up, and speak clearly.

Photo: cottonbro studio / Pexels
A retrospective study at Liverpool Hospital in Sydney, published in the Journal of Clinical Medicine in 2024, put numbers on the gap. Among 556 stroke-code patients with 164 MRI-confirmed ischemic strokes — 46 of them posterior-circulation — the results were stark:
- Sensitivity for posterior-circulation stroke: BE-FAST 97.8% vs FAST 58.7%
- 39.1% of those posterior-circulation strokes (18 patients) would have been missed by FAST alone
- Specificity: BE-FAST 10.0% vs FAST 39.8%
That third line is the honest catch, and I’d rather state it than bury it. Adding Balance and Eyes produces far more false alarms. A lot of dizziness is not a stroke. Broader reviews put FAST’s overall stroke detection somewhere around 69–90%, while missing up to 40% of posterior events — so the trade-off is real in both directions.
For a doctor, that trade-off is a genuine debate. For you, standing in a kitchen at 9 p.m., it isn’t close.
An unnecessary 911 call is a far smaller harm than a missed stroke.
One more note on the mnemonics themselves: there is no single global standard. The AHA/ASA leads with B.E. F.A.S.T., while the NHS in the UK still uses FAST (Face, Arms, Speech, Time to call 999). Both are pointing at the same emergency. The longer version simply casts a wider net — and yes, a longer acronym is harder to remember under pressure, which is an active area of study rather than a settled question.
Other sudden symptoms that mean the same thing
The word doing the work in every line below is sudden. All of these warrant an immediate 911 call:
- One-sided weakness or numbness — face, arm, or leg
- Sudden confusion, trouble understanding speech, or trouble finding words
- Sudden trouble seeing in one or both eyes
- Sudden severe dizziness, loss of balance, or inability to walk
- Sudden severe headache with no known cause, often with nausea or vomiting
That last one deserves its own paragraph. A “thunderclap” headache — the worst headache of someone’s life, peaking within seconds — is the hallmark of a subarachnoid hemorrhage. Neck stiffness, light sensitivity, and reduced alertness point the same direction. And a severe sudden headache that resolves on its own can be a “sentinel headache” preceding a major bleed.
It is still an emergency after it stops hurting.

Photo: kaboompics.com / Pexels
What to do — and what not to do — in the first minutes
Everything in this section is the opposite of what instinct suggests. Instinct says get in the car. Instinct says give them an aspirin. Instinct says let’s see if it passes.
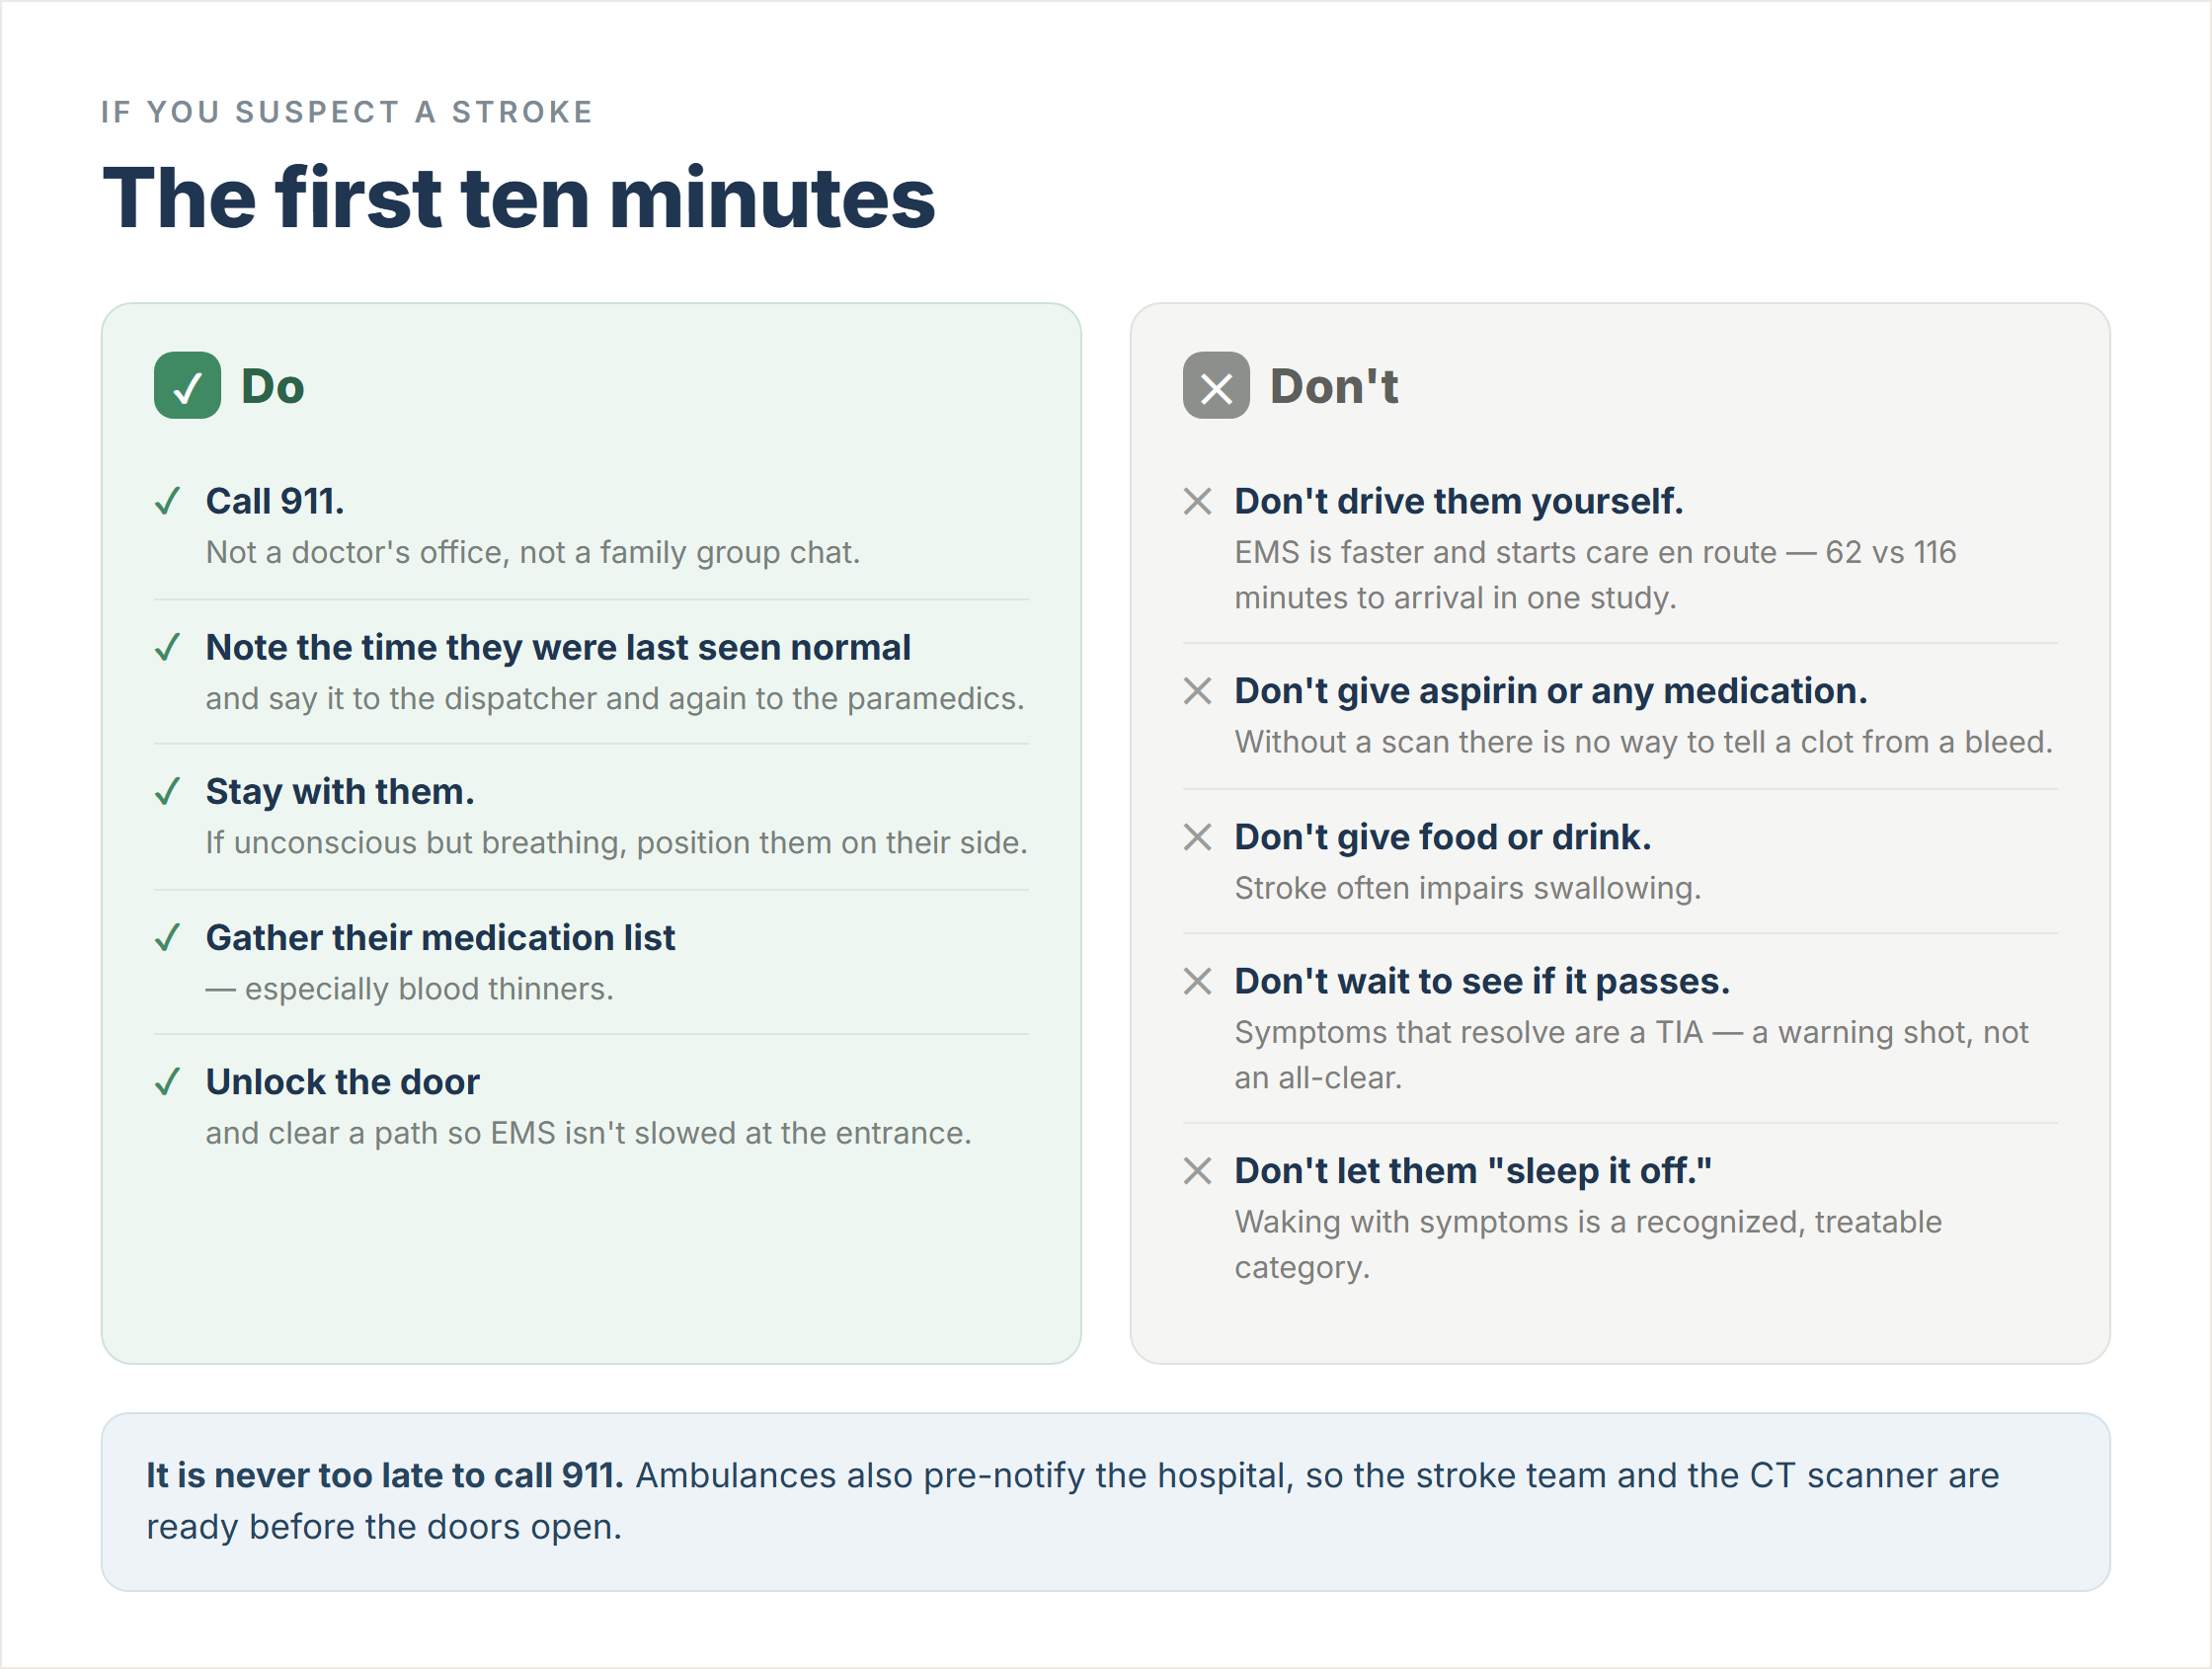
Do this:
- Call 911. Not a doctor’s office, not a family group chat. 911.
- Note the time they were last seen normal, and say it out loud to the dispatcher and again to the paramedics.
- Stay with them. If they’re unconscious but breathing, position them on their side.
- Gather their medication list — especially blood thinners. This directly affects treatment decisions.
- Unlock the door and clear a path, so EMS isn’t slowed at the entrance.
Do not do this:
| Don’t | Why |
|---|---|
| Don’t drive them yourself | EMS is measurably faster and starts care en route. In one study, patients who used EMS had a median onset-to-arrival time of 62 minutes vs 116 minutes for those who got there on their own — roughly twice the odds of arriving within two hours. |
| Don’t give aspirin or any medication | Without a scan, there is no way to tell an ischemic stroke from a bleed — and aspirin can make a bleed worse. Cleveland Clinic’s guidance is explicit: no food, no water, no medication including aspirin. Antithrombotic decisions come after the CT. |
| Don’t give food or drink | Stroke often impairs swallowing, which creates a real aspiration risk. |
| Don’t wait to see if it passes | Symptoms that resolve are a TIA — a warning shot, not an all-clear. Waiting also burns the treatment window. |
| Don’t let them “sleep it off” | Waking with symptoms is now a recognized, treatable category. Sleeping through it forfeits that. |
The EMS point is worth expanding, because “I’ll just drive, the hospital is ten minutes away” sounds so reasonable.
Ambulances don’t only transport. They pre-notify the hospital, so the stroke team, the CT scanner, and the neurologist are ready before the doors open. Studies of prehospital notification have found substantially shorter in-hospital delays with it than without — one multicenter study reported door-to-needle times of 42 minutes with pre-notification versus 70 minutes without; another reported 20 versus 29 minutes. EMS can also route to a hospital equipped for the specific treatment needed, which a family member driving cannot do.
Current AHA/ASA systems-of-care guidance goes further in the same direction: mobile stroke units — CT-equipped ambulances that can begin clot-dissolving treatment on the road — now carry a Class 1 recommendation, and direct transport to the nearest thrombectomy-capable hospital should be considered depending on the local system.
As the AHA puts it: calling 911 is the fastest way to get stroke care.

Photo: RDNE Stock project / Pexels
The real treatment windows
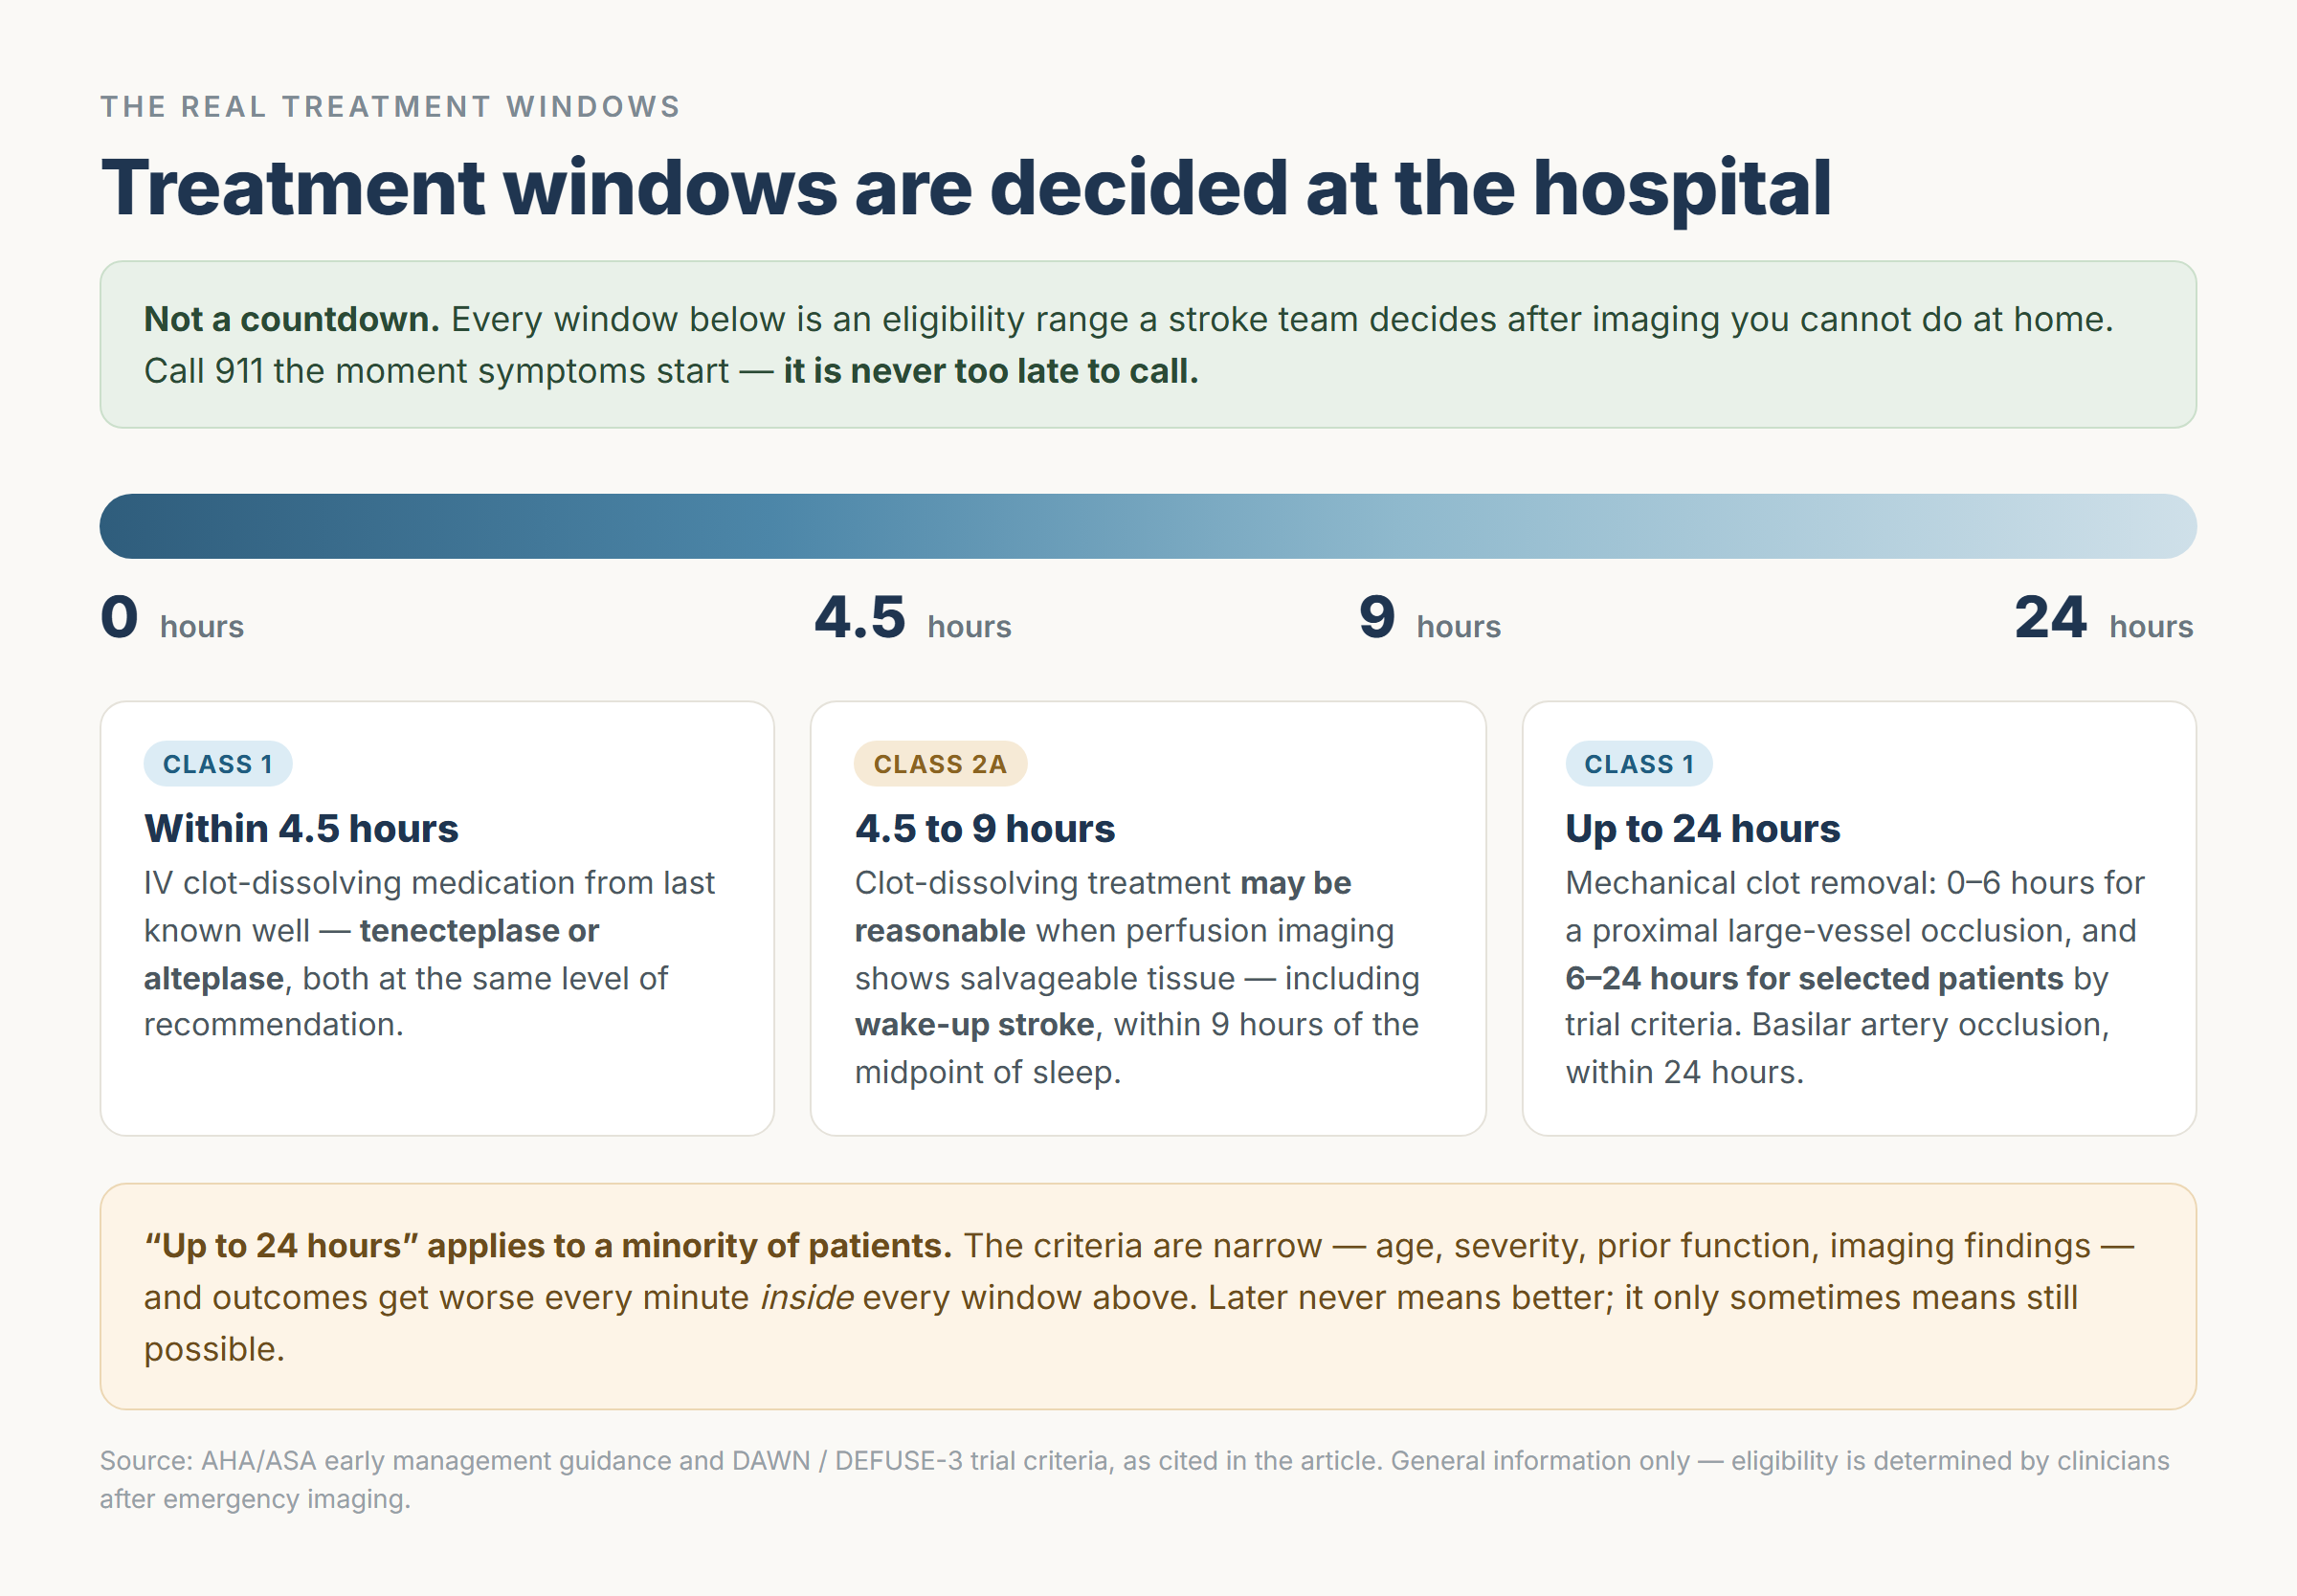
Now the numbers I had wrong. Read this section for orientation, not as a self-assessment tool — every one of these windows is an eligibility range that a stroke team decides, after imaging.
Within 4.5 hours — clot-dissolving medication
Current AHA/ASA guidance makes IV thrombolysis a Class 1 recommendation within 4.5 hours of last known well. Two drugs now stand equal at that level: tenecteplase and alteplase, both dosed by body weight by the treating team.
The practical difference is speed of delivery. Tenecteplase is a single IV bolus; alteplase requires a bolus plus an hour-long infusion. That makes tenecteplase faster to give and easier to run alongside preparations for clot removal.
A few things follow that are worth knowing:
- Treatment is recommended for eligible patients with disabling deficits regardless of stroke severity score.
- Treatment should not be delayed to obtain advanced vessel or perfusion imaging.
- Under 4.5 hours, patients are eligible regardless of those advanced findings.
Where did “3 hours” come from, then? It reflects the original trial window from the 1990s. Guidelines moved past it years ago — the number simply outlived its accuracy in public messaging, the way old health facts tend to.
4.5 to 9 hours — and waking up with symptoms
This is the one that surprised me most.
Clot-dissolving treatment may be reasonable (Class 2a) for patients whose perfusion imaging shows salvageable tissue, in either of two situations: those 4.5 to 9 hours from last known well, or those who woke up with symptoms, within 9 hours of the midpoint of their sleep. Selection is made on imaging — DWI-FLAIR or perfusion mismatch.
So the sentence “she woke up with it, so it’s too late” is wrong. Wake-up stroke is a recognized treatment population now.
But notice what determines it: a scan, in a hospital. There is no home version of this decision. That’s the argument for going immediately rather than debating it at the kitchen table.
Up to 24 hours — mechanical clot removal
Endovascular thrombectomy (EVT) physically removes a clot through a catheter. Its windows are the longest of all:
| Window | Current guidance |
|---|---|
| 0–6 hours | Class 1 for selected patients with a proximal large-vessel occlusion in the front circulation |
| 6–24 hours | Class 1 for selected patients, based on trial criteria including age, stroke severity, prior function, and imaging |
| Basilar artery occlusion | Class 1 within 24 hours in selected patients |
| Very large core, 6–24 hours | Still investigational |
The 6–24 hour window rests on the DAWN and DEFUSE-3 trials, which showed benefit for late-presenting large-vessel occlusion in patients selected by imaging and clinical mismatch.
And now the caveat that has to travel with all of it.
“Up to 24 hours” applies to a minority of patients. The criteria are specific and narrow — age limits, severity thresholds, prior independence, imaging findings. Most people who arrive late will not qualify. Meanwhile, outcomes get worse every minute inside every window listed above. Later never means better; it only sometimes means still possible.
So here is how I’d hold both halves at once:
There is no single number. 4.5 hours is the standard drug window, up to 9 hours for imaging-selected drug treatment including wake-up stroke, up to 24 hours for imaging-selected clot removal. The only rule that belongs in a household is: call 911 the moment symptoms start, and note when the person was last seen normal.
A TIA is an emergency even after it stops
A transient ischemic attack — a “mini-stroke” — produces stroke symptoms that resolve, often within minutes. Which is precisely why it gets ignored. The face straightens out, the words come back, everyone exhales.
The relief is the danger.
Stroke risk in the 90 days after a TIA runs as high as 17.8%, and nearly half of those strokes occur within 2 days of the original event. The risk is at its peak in the first 48 hours.
An AHA scientific statement on TIA in the emergency department is clear about what should happen: most patients with a suspected TIA should be sent to an emergency department, with a comprehensive evaluation ideally within 24 hours of symptom onset and neurology follow-up within 48 hours — no longer than a week.
The NHS says it more bluntly for the public: if you’ve had signs of a stroke within the last 24 hours, even if they have now stopped, get emergency help straight away.

Photo: Pixabay / Pexels
There’s a treatment reason for the urgency too. For minor stroke or high-risk TIA of atherosclerotic cause, current guidance considers a short course of dual antiplatelet therapy reasonable — but it’s a physician-prescribed, time-limited regimen started after imaging. It is not something anyone should start from a medicine cabinet.
Risk factors, and the one you can’t feel
About 80% of strokes are preventable, according to the AHA — and nearly 1 in 4 strokes occur in people who have already had one. Prevention is not a footnote to this topic. It’s most of it.
The leading modifiable risk factors, per the CDC:
- High blood pressure — the leading cause of stroke, and the main driver of elevated risk in people with diabetes
- Diabetes
- Smoking
- High cholesterol, obesity, physical inactivity, heavy alcohol use
- Atrial fibrillation
Age matters too — risk climbs sharply after 55 to 65 — along with family history and a prior stroke or TIA.
The atrial fibrillation problem
AFib deserves its own heading because of how it hides.
AFib causes about 1 in 7 strokes (CDC), and after adjusting for other risk factors it’s associated with roughly a five-fold increase in ischemic stroke risk. Untreated, it carries something like a 5% annual stroke risk.
And it is frequently asymptomatic.
That’s the whole problem in three words. For a meaningful number of people, the stroke is how they find out. Which makes the unglamorous things matter: checking a pulse, paying attention when a wearable flags an irregular rhythm, getting the ECG your doctor suggested and didn’t push hard on.
On treatment, the 2023 ACC/AHA/ACCP/HRS atrial fibrillation guideline shifted toward basing anticoagulation decisions on the magnitude of estimated risk rather than a score alone, recommending therapy when estimated annual stroke risk reaches about 2% or higher. DOACs are preferred over warfarin, except in mitral stenosis or mechanical heart valves, where warfarin remains necessary. For context on the size of the effect, oral anticoagulation provides roughly a 40% reduction in recurrent stroke compared with antiplatelet therapy.
All of which is a conversation with your own physician, not a decision to make from a blog post.

Photo: Vlada Karpovich / Pexels
What I’d want my own family to remember
If you only keep three things from all of this, keep these.
The checklist is six letters, not three. Balance and eyes belong in it, because a stroke in the back of the brain can leave the smile and the handshake perfectly intact.
The clock you need is “last seen normal.” Not when you noticed, not when you called. Say it to the dispatcher, say it again to the paramedics, and don’t apologize for being unsure — a range is better than nothing.
And the windows are not a countdown you’re allowed to lose. Four and a half hours, nine hours, twenty-four hours — those are ranges a stroke team works within, using scans, on a minority of patients. They exist so that arriving late still gets evaluated. They do not exist to make waiting reasonable.
I spent years quietly confident about three hours and three tests. What actually mattered was much simpler than the number I was proud of knowing, and I’d rather hand it over plainly.
If something changes suddenly in someone’s face, arm, speech, balance, or vision — you don’t need to work out which kind of stroke it is, or whether you’re still inside a window, or whether you might be overreacting.
You just call.
Medical disclaimer. This article is general health information for education, not medical advice, and it is not a diagnostic tool. If you suspect a stroke in yourself or someone else, call 911 immediately — do not use this page to decide whether symptoms are serious enough, and do not use the time windows described here to decide whether it is “too late” to seek care. Treatment eligibility, including every window mentioned, is determined by clinicians after emergency imaging. Do not start, stop, or change any medication — including aspirin or blood thinners — without your own physician.
References
- AHA/ASA — 2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke (Stroke 2026;57(8), superseding the 2018 guideline and 2019 update). Guideline figures here are drawn from AHA’s own science-news summary and independent clinician summaries rather than the full text, which was not directly accessible; nothing above is presented as a direct quotation.
- American Stroke Association — B.E. F.A.S.T. materials; Stroke Symptoms and Warning Signs; AHA American Stroke Month release (May 2026)
- Saver JL, Stroke (2006) — Time Is Brain, Quantified
- Journal of Clinical Medicine (2024) — BE-FAST vs FAST in identifying posterior circulation strokes (Liverpool Hospital, Sydney; n=556)
- British Journal of Community Nursing — BE-FAST vs FAST in prehospital stroke recognition: a systematic review
- CDC — Stroke Facts; Risk Factors for Stroke; About Atrial Fibrillation
- AHA Scientific Statement, Stroke — Diagnosis, Workup and Risk Reduction of Transient Ischemic Attack in the Emergency Department Setting
- NHS UK — Stroke: Symptoms
- Cleveland Clinic — Hemorrhagic Stroke; Ischemic Stroke
- ACC — 2023 ACC/AHA/ACCP/HRS Atrial Fibrillation Guideline, Key Perspectives
- PMC / PubMed — Effect of prehospital notification on acute stroke care (multicenter); Use of Emergency Medical Services and Timely Treatment Among Ischemic Stroke Patients





